 Nephrology
 Urology
 Andrology
 Fertility (IVF)
 General Nephrology
 Paediatric Nephrology
 Dialysis
 Renal (Kidney) Biopsy
 CRRT
 Peritonial Dialysis
 Robotic Surgery
 Urinary Incontinence
 Uro-Oncology
 Laparoscopic Urology
 Reconstructive Urology
 Anaesthesiology
 Radiodiagnosis
 Nutrition and Dietetics
 Pediatric and Immunization
 Cardiology
 Intensive Care Unit




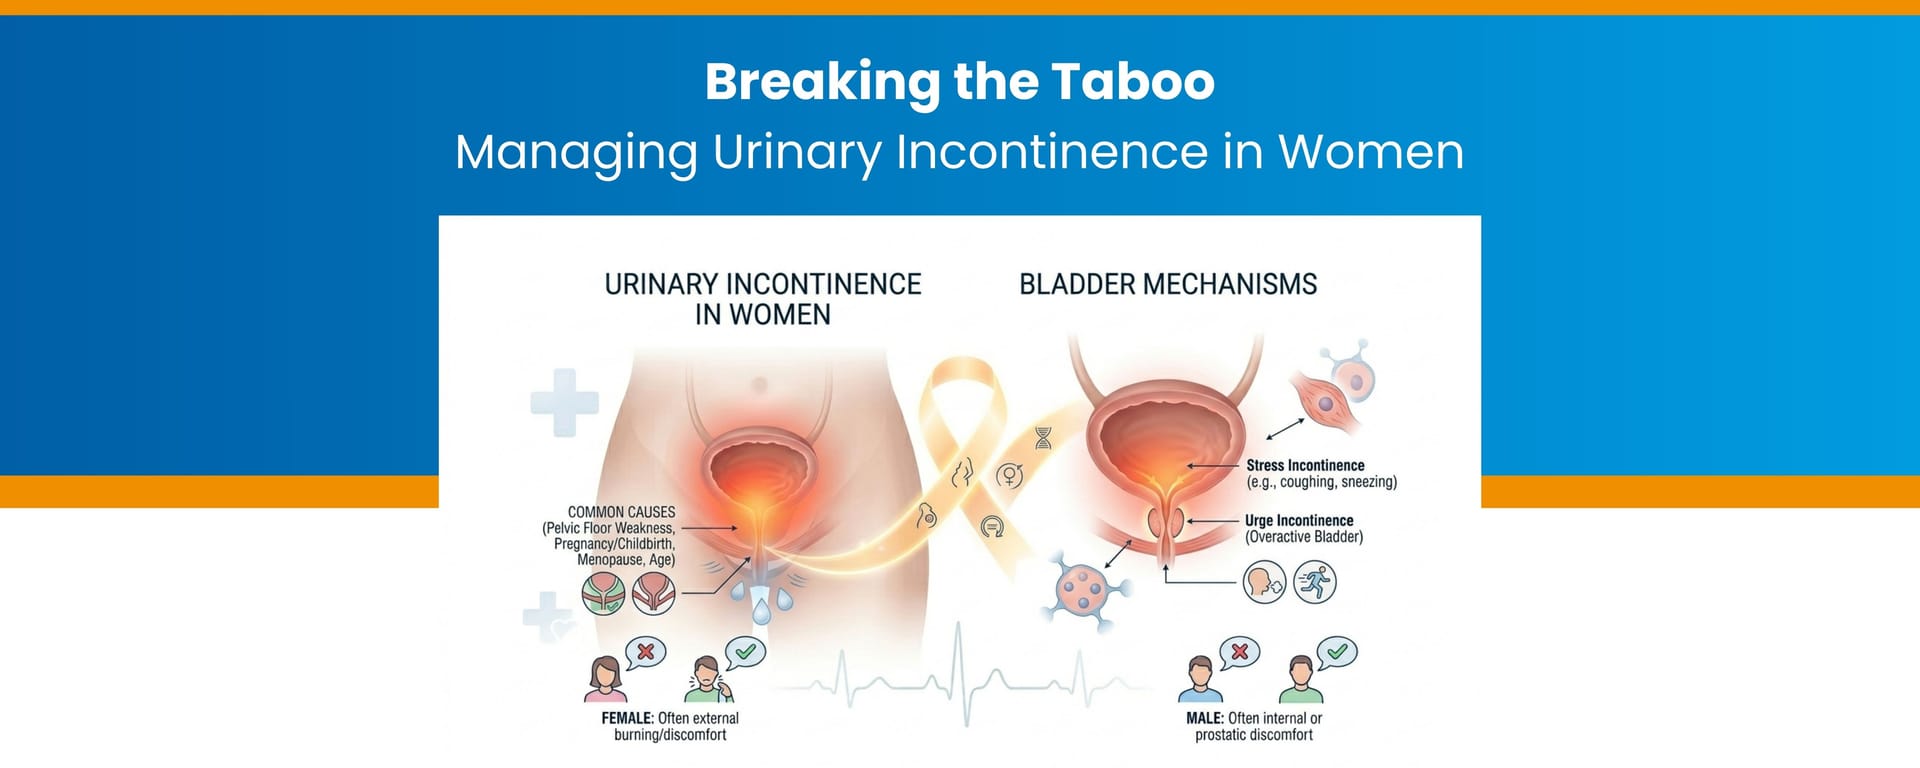
Breaking the Taboo: Managing Urinary Incontinence in Women
For many women, a sneeze, a sudden burst of laughter, or even a hasty jog can cause an embarrassing situation. Urinary leakage is a common condition; however, it remains one of the least reported health issues due to the social stigma associated with it. Many women live in silence, believing that loss of bladder control is a natural consequence of giving birth or ageing as a natural process.
But medical science says otherwise. The problem of female urinary incontinence is not a normal life cycle and should not be tolerated, but it is a treatable condition. The first step to regaining confidence is to break the silence. When women learn that bladder leakage may be treated, they can seek medical care and begin treatment. Modern urology offers an extensive range of solutions, including simple lifestyle adjustments and major surgical treatments, to improve quality of life.
Understanding the Silence: Why Women Wait?
The stigma associated with bladder disorders prevents women from getting help for an extended period of time. Many women reorganise their lives around the condition - wearing dark clothes, locating nearby public toilets, or dropping the physical engagements they previously enjoyed. This silent coping may cause skin irritation, urinary tract infections, and a significant impact on mental well-being.
At NU Hospitals, the emphasis remains on a discreet and supportive environment. The clinical team understands that no two women have the same experience and therefore believes in caring with empathy and a personalised approach. By addressing female urinary incontinence openly, medical professionals help patients reclaim their freedom.
Mechanics of the Pelvic Floor
The female pelvic floor is a network of muscles and ligaments that support the bladder, uterus, and bowel. These muscles function like a hammock, which maintains the pelvic organs in their proper place. The support system fails when these muscles become weak or damaged, usually during pregnancy, vaginal birth, or menopause, due to hormonal changes.
A weakened support system leads to various forms of leakage. In some cases, the bladder is no longer in its natural position, resulting in a prolapse. In other cases, the urethral sphincter, or the valve that holds the bladder closed, is just too weak to withstand the pressure. Treatment of these underlying causes with pelvic floor repair or other targeted interventions may frequently eliminate symptoms.
Types of Urinary Incontinence
Not all leakage is the same. It is critical to understand the type of incontinence to select the appropriate bladder leakage treatment. The cause might range from a weak pelvic muscle to overactive nerve impulses.
Type of Incontinence |
Primary Characteristics |
Common Triggers |
Stress Incontinence |
Leakage due to physical pressure on the bladder. |
Coughing, sneezing, lifting, or exercising. |
Urge Incontinence |
A sudden, intense need to urinate followed by involuntary leakage. |
Hearing running water or sudden temperature changes. |
Overflow Incontinence |
The bladder doesn’t empty, leading to frequent "dribbling." |
Blockages or weakened bladder muscles. |
Functional Incontinence |
Physical or mental impairments prevent reaching the toilet in time. |
Arthritis or mobility issues. |
Mixed Incontinence |
A combination of both stress and urge symptoms. |
Various physical and neurological triggers. |
The Pathway to a Bladder Leakage Treatment
The first step to a successful recovery is accurate diagnosis. Various tools are used by urologists and urogynecologists to assess the cause and severity of leakage.
1. Bladder Diary:
The patient logs fluid intake, the time of urination, and how often urine leaks over a few days. This provides practical insight into bladder behaviour.
2. Physical Examination:
A doctor analyses symptoms of organ prolapse in the pelvic region or muscle weakness.
3. Urodynamic Testing:
It is a complex test that measures bladder pressure and urine flow to determine whether the bladder can comfortably contain and expel urine.
4. Cystoscopy:
This involves a small camera that allows the doctor to inspect the interior of the bladder to identify inflammation or structural abnormalities.
Non-Surgical Management and Lifestyle Changes
Surgery is not always the first or only solution for many women. In mild-to-moderate cases of female urinary incontinence, conservative interventions can be of great benefit.
Pelvic Floor Muscle Training (Kegels)
The most effective non-surgical approach involves strengthening the "hammock" of muscles. Such exercises improve support for the bladder and urethra when performed properly and consistently. Specialist physical therapists often use biofeedback to ensure the correct muscles are activated.
Behavioral Modifications
The frequency of urges can be reduced by regulating fluid intake and avoiding bladder irritants such as coffee, alcohol, and highly acidic foods. Bladder retraining that involves urinating at set intervals helps the bladder retain more urine over time.
Topical Estrogen Therapy
In post-menopausal women, leakage is caused by the thinning of the vaginal and urethral tissues caused by low estrogen. These tissues can be restored to health with topical estrogen creams to strengthen the urethral seal and reduce urge symptoms.
Surgical Solutions: Stress Incontinence Surgery and Repair
Surgical interventions have a high success rate when conservative measures fail. These surgeries seek to give the bladder and urethra the permanent support that they do not have.
Sling Procedures
The most common type of surgery performed to treat stress incontinence is the insertion of a urethral sling, which can be made of mesh or natural tissue. This acts like a supportive hammock that helps hold up the urethra during physical activity, preventing leakage. Mid-urethral slings are the least invasive and may lead to a fast recovery.
Pelvic Floor Repair
If the leaking is caused by pelvic organ prolapse (when the bladder or uterus prolapses into the vaginal canal), a more thorough pelvic floor repair may be necessary. Surgeons use various techniques to lift and secure the organs back into their anatomical positions.
A Legacy of Expertise: The Autologous Sling
NU Hospitals has a strong reputation in the field of pelvic floor repair. The first Autologous Pubovaginal Sling was done in the Malnad region by the institution. An autologous sling is different, as it is made from the patient's own tissue (fascia) rather than a synthetic mesh. This reduces the risk of rejection and delayed complications, demonstrating a deep commitment to patient care and surgical precision.
In complex cases, robotic-assisted surgery enables the placement of such supports with greater precision, leading to smaller incisions and shorter recovery times.